Solution Database / Healthcare
Medical inventory planning tool
Ordering decisions overlook usage patterns and expiry dates. Small-clinic planning combines consumption with expiry and storage constraints.
01The offer
For clinic operations managers buying routine supplies, turn supply usage, stock counts and supplier lead times into reviewed replenishment suggestions. Address the recurring problem: ordering decisions overlook usage patterns and expiry dates. The value hypothesis is a more complete, reviewable deliverable with less repeated preparation; the pilot must establish whether that benefit is real.
- For
- Clinic operations managers buying routine supplies
- Takes in
- Supply usage, stock counts and supplier lead times
- Delivers
- Reviewed replenishment suggestions
- Message
- Medical inventory planning tool for clinic operations managers buying routine supplies. Small-clinic planning combines consumption with expiry and storage constraints. Demonstrate the claim through a supply usage and expiry review.
- Lead magnet
- A supply usage and expiry review
02How it works
- Normalize supply items
- Flag expiring stock
- Model usage
- Account for lead times
- Suggest order quantities
- Record staff approval
Workflow
Validate baseline inputs, confirm definitions and constraints, select editable assumptions, calculate feasible alternatives, inspect sensitivities, let the responsible person approve a plan, and compare later actuals with the recorded assumptions. Start with supply usage, stock counts and supplier lead times and finish with reviewed replenishment suggestions.
AI and people
Extract input context and explain scenario differences. Use deterministic calculations or explicit optimization for quantities, compatibility, dates and prices. Show uncertain assumptions. Never let generated prose silently change the calculation rules.
Screens
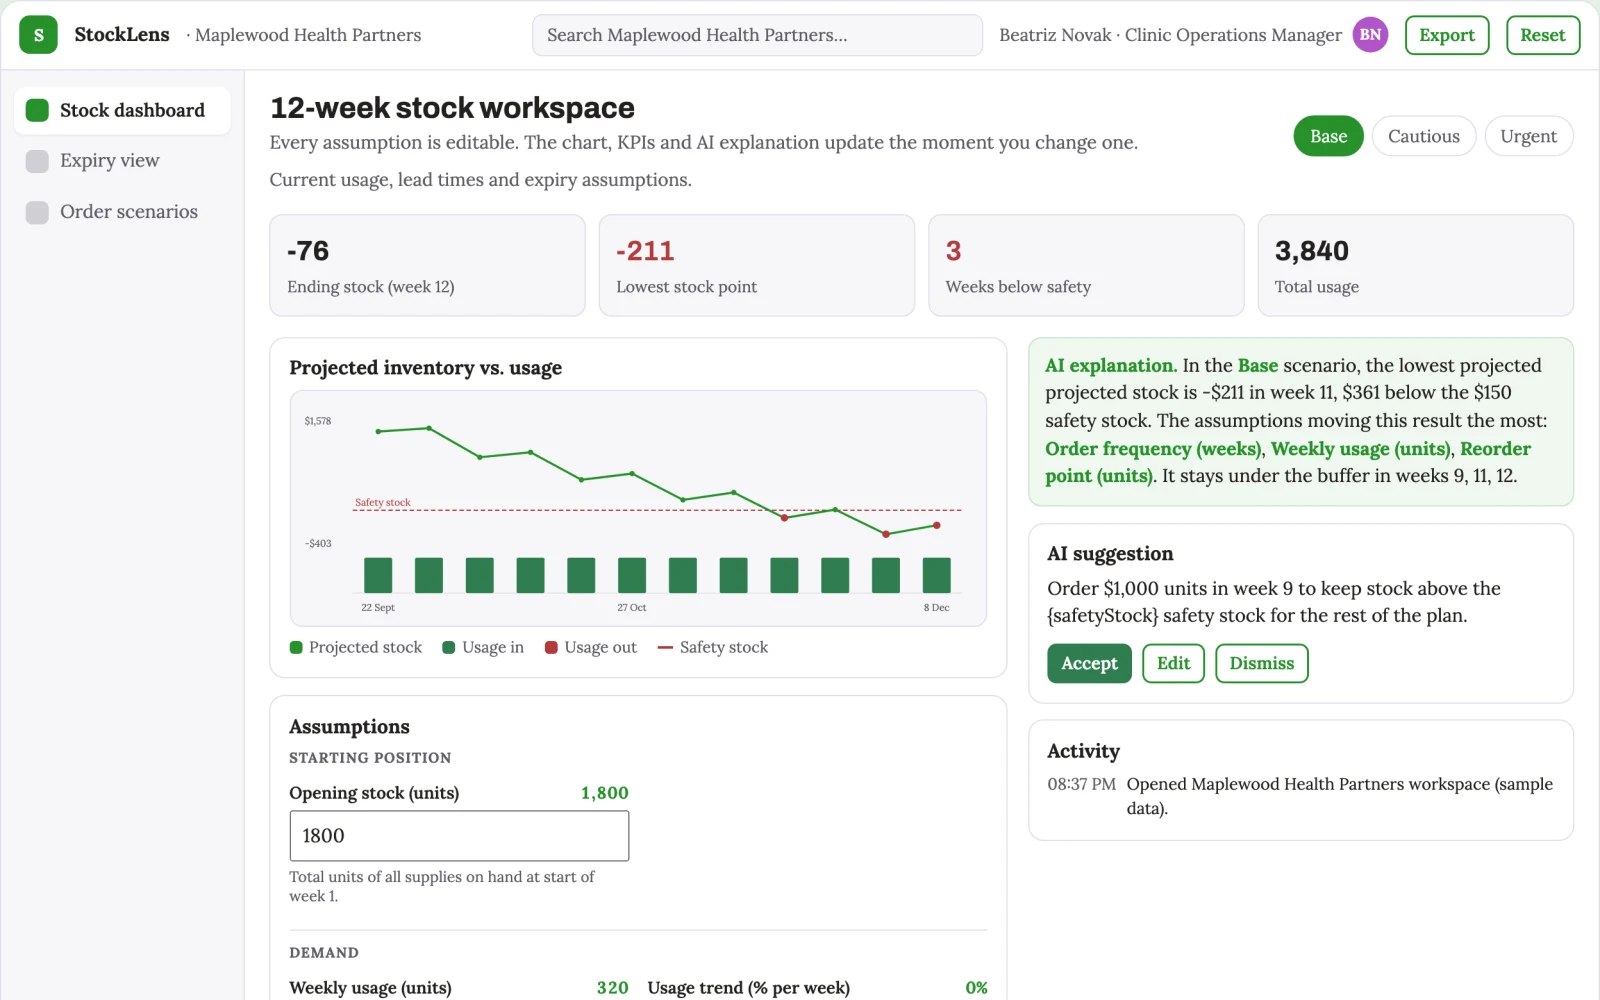
Key screens: Stock dashboard, expiry view, order scenarios. Place editable drivers and constraints beside a clearly labeled scenario output. Include a baseline view, comparison chart or schedule, and an assumptions history. Let users trace a proposed quantity or date back to its inputs. Keep forecasts distinct from actual results. In this product, the first view is stock dashboard, followed by expiry view and order scenarios.
Admin
Scenario versions, baseline reconciliation, constraint checks, assumption ownership, reviewer approvals, plan exports and actual-versus-plan tracking.
03Market gap
Alternatives buyers use today
Spreadsheets, planners, specialist forecasting tools and existing scheduling or configuration software. Differentiate on this specific proposed advantage: small-clinic planning combines consumption with expiry and storage constraints. Test it against the buyer's current method on the same task. Competitor coverage and uniqueness have not been established.
Where this wins
A validated domain model, customer-approved constraints and forecast or decision history that improves practical planning. For this solution, build around small-clinic planning combines consumption with expiry and storage constraints. This advantage requires execution and accumulated customer trust; the base model alone is not a defensible asset.
04Why now
Healthcare teams are adopting AI for exactly this kind of repeatable work, and the cost of language and vision models has dropped far enough that a narrow, reviewed workflow pays back quickly. The buyer already feels the problem: ordering decisions overlook usage patterns and expiry dates.
05Proof & signals
Channels where buyers gather: Medical supply distributors. Metrics that prove it works: Stockouts, expired stock value.
Paid pilot
Reproduce a known historical plan, test missing inputs and boundary constraints, then run a new scenario. Compare feasibility, reconciliation and observed error rather than judging the quality of the explanation alone. For this solution, use supply usage, stock counts and supplier lead times and evaluate reviewed replenishment suggestions. Agree success thresholds with the buyer before starting; collect a baseline for stockouts, expired stock value. A positive signal is payment and repeat use with acceptable quality and delivery cost, not a favorable demo reaction alone.
06Execution plan
MVP
Begin with clinic operations managers buying routine supplies and one recurring use case. Build the first two modules: normalize supply items; flag expiring stock. Provide operator assistance for the third module: model usage. Deliver reviewed replenishment suggestions through a manual review queue. Perform other necessary full-scope functions manually during the pilot. Include all applicable access, accuracy and professional-review controls from the start.
First 30 days
Week 1: interview five prospective buyers in this segment: clinic operations managers buying routine supplies. Ask to see a recent example of the problem and their current process. Week 2: prepare this demonstration using authorized or synthetic material: a supply usage and expiry review. Week 3: present it through medical supply distributors and seek one narrowly scoped paid pilot. Week 4: review stockouts, expired stock value, total delivery effort and a concrete renewal decision before increasing scope.
After the pilot
After paid pilots establish value, automate the remaining modules: account for lead times; suggest order quantities; record staff approval. Add one validated source integration, reusable customer configuration and recurring delivery. Expand to additional teams, document formats or languages only after testing the new scope.
Retention
Refresh inputs, compare recorded assumptions with actual outcomes and refine validated constraints. Expand scenario complexity only when the buyer uses it for a decision.
Integrations
Clinic-approved content and administrative exports. Clinical integrations require separate assessment. Read-only operational exports, calendars and finance or inventory records as relevant. Start with plan exports and retain human approval for execution. These are candidate integration categories, not verified supported connectors.
07Investment and running costs
| Phase | Scope | Time | Budget |
|---|---|---|---|
| MVP | One buyer segment, one recurring use case; first modules: normalize supply items; flag expiring stock. Manual review in the loop. | 7 days | $11,500 |
| Paid pilot | Accounts, roles, review states, audit trail and the first integration, hardened for two to three paying pilot customers. | 8 days | $15,000 |
| Full product | Remaining modules: account for lead times; suggest order quantities; record staff approval. Self-serve onboarding, billing, monitoring and the wider integration set. | 3 weeks | $20,500 |
| Total | $47,000 | ||
| Running | Hosting | AI usage | Total a month |
|---|---|---|---|
| MVP and paid pilot (about 3 customers) | $50–$100 | $50–$100 | $100–$200 |
| Full product (about 50 customers) | $190–$380 | $350–$700 | $540–$1,080 |
Revenue model to test
Test USD 750-3,000 for a scoped planning setup and review, then USD 200-900 monthly for refreshes within agreed complexity. Data integration and optimization are separately scoped. All ranges are hypotheses.
Cost drivers
Data preparation, domain modeling, validation, scenario computation, reviewer support and ongoing assumption maintenance.
Safeguards
Begin with administrative scope or clinician-reviewed material. Minimize sensitive patient data, restrict access and obtain required organizational review before connecting clinical systems. Validate source access and reviewer availability during the pilot. Maintain customer-level access, data deletion controls and a record of final approvals.
Take it further
Concept proposal expanded from the 315-solution conversation. Demand, pricing, differentiation, build scope and integration feasibility are hypotheses, not verified market findings. Category link is inspiration rather than evidence of business viability.