Solution Database / Healthcare
Discharge instruction comprehension lab
Approved discharge leaflets are hard to test for patient comprehension. Test understanding of approved instructions before wider use.
01The offer
For hospital patient-education teams, turn clinician-approved instructions and comprehension rubrics into clinician-reviewed comprehension report. Address this specific problem: approved discharge leaflets are hard to test for patient comprehension. The aim: test understanding of approved instructions before wider use. The pilot tests whether that benefit holds up against reviewer effort and real operating costs.
- For
- Hospital patient-education teams
- Takes in
- Clinician-approved instructions and comprehension rubrics
- Delivers
- Clinician-reviewed comprehension report
- Message
- Test understanding of approved instructions before wider use. Demonstrate the result with review one discharge leaflet with volunteers for hospital patient-education teams. Use a concrete before-and-after example without promising unmeasured savings.
- Lead magnet
- Review one discharge leaflet with volunteers
02How it works
- Extract action steps
- Flag ambiguous wording
- Draft teach-back questions
- Compare reading variants
- Capture patient feedback
- Export revision proposals
Workflow
The buyer creates a project, supplies clinician-approved instructions and comprehension rubrics, and confirms scope and access. The working sequence is: 1. Extract action steps. 2. Flag ambiguous wording. 3. Draft teach-back questions. 4. Compare reading variants. 5. Capture patient feedback. 6. Export revision proposals. Users correct extracted facts, resolve flagged uncertainties and approve the final clinician-reviewed comprehension report before use. Retain source links and a version history for the next cycle.
AI and people
Suggest clarity improvements that clinicians verify for preserved meaning. Keep model suggestions separate from verified facts. Link factual outputs to authorized input evidence and show missing information explicitly. Use deterministic checks for counts, dates, identifiers and arithmetic where applicable. A designated reviewer validates consequential outputs and signs off the delivered result.
Screens
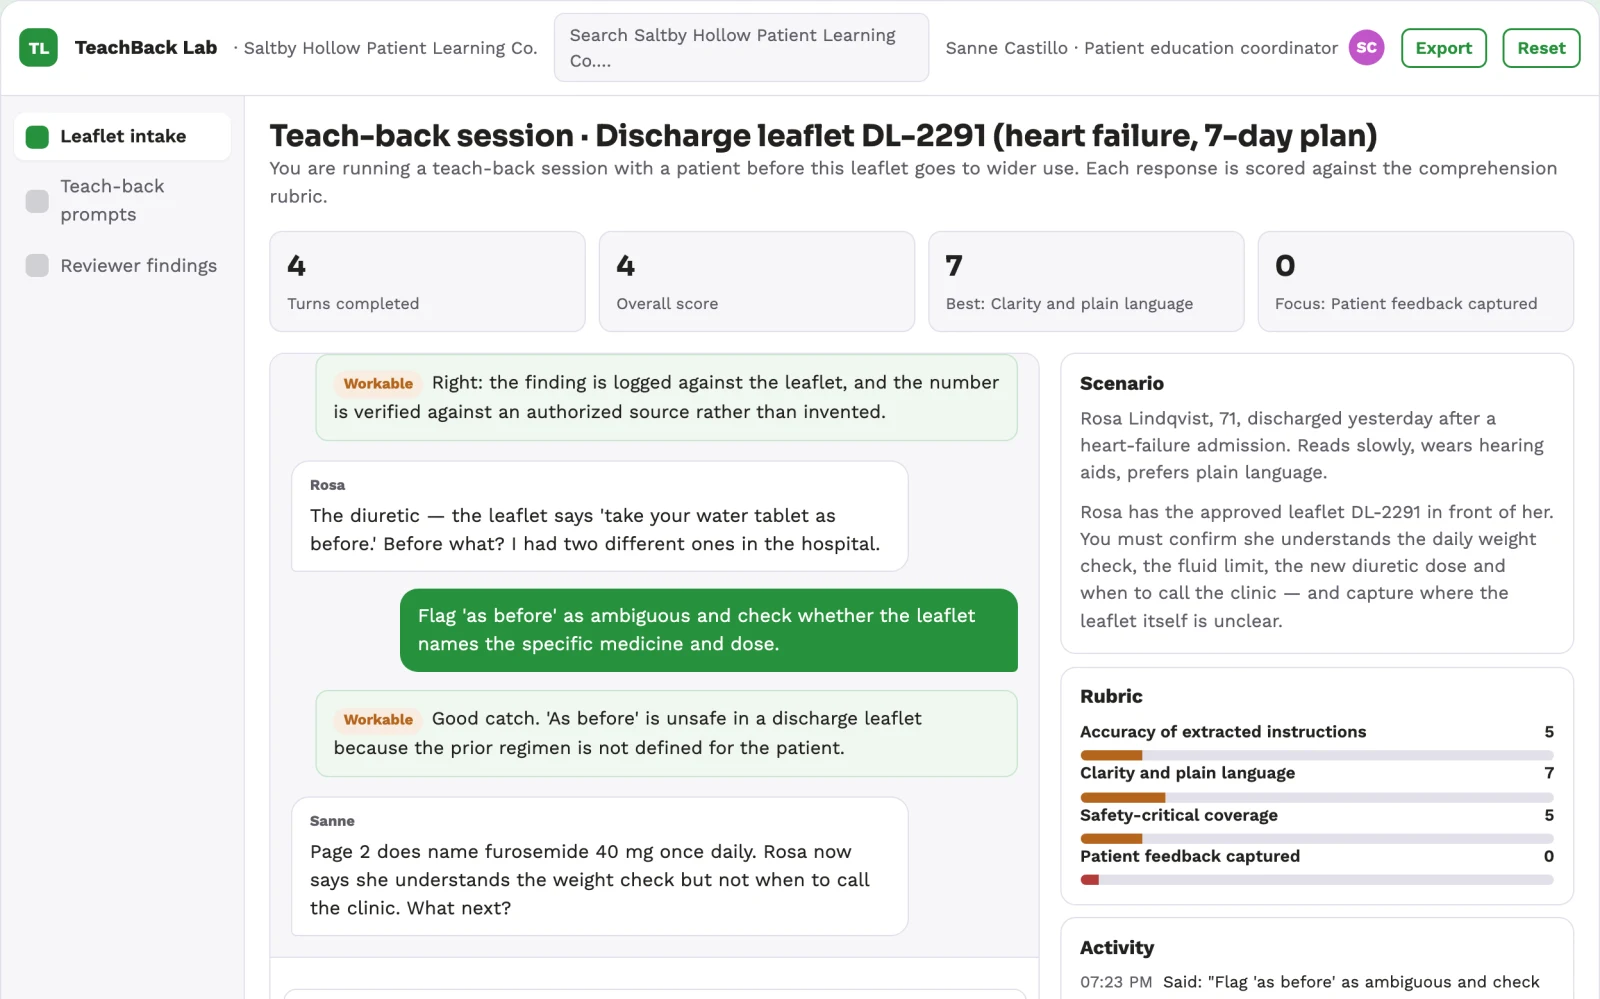
Key screens: Leaflet intake, Teach-back prompts, Reviewer findings. Use a scenario catalog with clear goals and difficulty settings. The main session area supports text, optional voice and visible context. Follow it with a replay or decision map, annotated feedback and a next-practice plan. Facilitators can author scenarios and review participant-selected sessions. Open with leaflet intake; move into teach-back prompts for the detailed task; finish in reviewer findings for review and handoff. Show the source record, uncertainty and approval status beside each proposed output.
Admin
Participant-controlled session sharing, scenario versions, facilitator tools, replay history, rubric calibration, practice goals and exportable feedback. Include organization-scoped access, named project owners, review queues, usage limits, export history and retention settings. Never reuse private customer material for other accounts without permission.
03Market gap
Alternatives buyers use today
Human coaching, workshops, static courses, roleplay with colleagues and general chat tools. Position this concept around test understanding of approved instructions before wider use. Compare it against the customer's current process on the same representative task. This is proposed differentiation; no exhaustive competitor study or uniqueness claim has been established.
Where this wins
Realistic domain scenarios, qualified facilitator relationships and reviewed examples of useful feedback and successful practice. For this concept, accumulate permissioned examples and reviewer corrections around test understanding of approved instructions before wider use. The durable asset is reliable task-specific execution and trusted customer configuration, not access to a general-purpose AI model.
04Why now
Healthcare teams are adopting AI for exactly this kind of repeatable work, and the cost of language and vision models has dropped far enough that a narrow, reviewed workflow pays back quickly. The buyer already feels the problem: approved discharge leaflets are hard to test for patient comprehension.
05Proof & signals
Channels where buyers gather: Patient experience teams and health literacy specialists. Metrics that prove it works: Observed misunderstandings and clinician correction rate.
Paid pilot
Agree the acceptance criteria, input limits and reviewer responsibilities before starting. Run review one discharge leaflet with volunteers and deliver clinician-reviewed comprehension report. Compare observed misunderstandings and clinician correction rate with the buyer's current process on comparable cases; include corrections, missed issues and reviewer time. Seek payment and repeat use. Stop or revise the scope if data access, accuracy or unit economics fail.
06Execution plan
MVP
Costed pilot: Content usability testing; no personalized medical advice. Start with one buyer organization and a bounded set of representative inputs. Implement the first two modules: extract action steps; flag ambiguous wording. Support the third task through an assisted review queue: draft teach-back questions. Handle the remaining required functions manually until validated. Include input upload, source references, user correction, a reviewer approval step and export of clinician-reviewed comprehension report. Authentication, account isolation, deletion controls and basic operational logging are included. Specialized production certification, live write integrations and broader rollout are not included unless explicitly stated.
First 30 days
Week 1: interview five prospective buyers from hospital patient-education teams and inspect how they handle approved discharge leaflets are hard to test for patient comprehension. Week 2: prepare review one discharge leaflet with volunteers using authorized or synthetic material. Week 3: share the demonstration through patient experience teams and health literacy specialists and seek one bounded paid pilot. Week 4: measure observed misunderstandings and clinician correction rate, review delivery effort and ask for a repeat purchase. This is a validation schedule, not a promise that the full product can be built in thirty days.
After the pilot
After paying customers repeatedly accept clinician-reviewed comprehension report, automate compare reading variants; capture patient feedback; export revision proposals. Add one tested read integration, reusable customer configuration and scheduled repeat delivery. Increase supported formats or teams only when evaluation cases and reviewer capacity cover the new scope. Content usability testing; no personalized medical advice.
Retention
Build repeat use around clinician-reviewed comprehension report. Save approved configurations and review decisions with permission, revisit unresolved exceptions and show progress on observed misunderstandings and clinician correction rate. Offer a recurring volume allowance after repeat demand; expand to adjacent tasks only when the buyer asks and delivery quality remains acceptable.
Integrations
Clinic-approved content and administrative exports. Clinical integrations require separate assessment. Learning portals, calendar scheduling and authorized session exports. Make recording, sharing and retention controls explicit in the product. Begin with uploads and exports of clinician-approved instructions and comprehension rubrics. Any named system or connector is a candidate requiring current access and compatibility checks; no live connection is included by default.
07Investment and running costs
| Phase | Scope | Time | Budget |
|---|---|---|---|
| MVP | One buyer segment, one recurring use case; first modules: extract action steps; flag ambiguous wording. Manual review in the loop. | 7 days | $13,000 |
| Paid pilot | Accounts, roles, review states, audit trail and the first integration, hardened for two to three paying pilot customers. | 8 days | $13,000 |
| Full product | Self-serve onboarding, billing, monitoring and the wider integration set. | 3 weeks | $18,000 |
| Total | $44,000 | ||
| Running | Hosting | AI usage | Total a month |
|---|---|---|---|
| MVP and paid pilot (about 3 customers) | $50–$100 | $50–$110 | $100–$210 |
| Full product (about 50 customers) | $190–$380 | $420–$840 | $610–$1,220 |
Revenue model to test
Test USD 300-1,500 for a facilitated team pilot, or USD 20-80 per participant monthly for self-serve practice with limited usage. Bespoke workshops and expert coaching are separately scoped. Pricing is hypothetical. For this buyer, package the first sale around review one discharge leaflet with volunteers and the defined clinician-reviewed comprehension report. Record actual review effort before offering a recurring allowance. The commercial pilot fee is distinct from the platform development budget.
Cost drivers
Scenario design, voice processing if used, model interaction length, facilitator review, rubric calibration and learner support. Initial validation additionally budgets for clinical review and volunteer facilitation. Track model usage, storage, reviewer minutes, exception handling and customer support per accepted deliverable.
Safeguards
Begin with administrative scope or clinician-reviewed material. Minimize sensitive patient data, restrict access and obtain required organizational review before connecting clinical systems. Content usability testing; no personalized medical advice. Require appropriate access and publication approval. Preserve source material, label AI drafts and make corrections traceable. Measure false positives and missed cases alongside speed.
Take it further
Newly authored additional batch of 210 concepts, dated 2026-09-22, for later import. Checked against the existing 413 catalog for exact title and ID duplication, with editorial review of overlap. Demand, differentiation, pricing, build hours, setup costs and integration feasibility are unvalidated planning hypotheses. Category inspiration links are inherited taxonomy references, not evidence that these concepts were covered there.